By ANEMONA HARTOCOLLIS
Published: September 16, 2008
A Manhattan dialysis center closed down after State Health Department inspectors found blood on chairs and machines and discovered that at least one patient had contracted hepatitis C because of the unsanitary conditions.
More than 600 other patients treated at the center, going back nearly five years, were urged to get hepatitis and H.I.V. tests.
Claudia Hutton, a spokeswoman for the Health Department, said on Tuesday that it inspected the clinic, the Life Care Dialysis Center, at 221 West 61st Street, for a week in mid-August and found that employees had failed to wash their hands properly, disinfect equipment or change gloves between patients. Inspectors also found blood on treatment chairs.
“It was repulsive,” Ms. Hutton said. “The treatment chairs that they gave people to relax in had someone else’s dried blood on them.”
Ms. Hutton said that the clinic was ordered to begin sending its patients to other clinics immediately while the Health Department began testing patients for signs of infection.
She said that when one patient was found to have been infected by hepatitis C, a liver disease, because of contaminated equipment, the clinic shut down voluntarily.
Richard F. Daines, the state’s health commissioner, sent letters on Monday to 657 patients of the clinic going back to January 2004, the last time infection-control violations had been found, urging them to be tested for possible exposure to hepatitis C, hepatitis B and H.I.V. The clinic, which had 171 patients at the time of the inspection, agreed to pay for the testing, even if it is done by private doctors, officials said.
Ms. Hutton said there was no evidence that other patients had been infected.
Dr. Walter Wasser, the clinic’s operator and medical director, was fined $300,000 and surrendered his operating certificate, Ms. Hutton said. He could face the loss of his medical license after an investigation by the State Office of Professional Medical Conduct, Ms. Hutton said. She declined to say whether such an investigation had begun.
Dr. Wasser did not return a call for comment left with his answering service.
Ms. Hutton said that the Health Department visited the clinic in August to follow up on previous violations, not because of any specific new complaints from patients. She said the department tried to inspect clinics once a year, but was sometimes not able to do so that often because of manpower shortages and the volume of complaints.
She said the department was particularly concerned about dialysis clinics because their patients have compromised immune systems that make them vulnerable.
http://www.nytimes.com/2008/09/17/nyregion/17dialysis.html?_r=2&ref=nyregion&oref=slogin&oref=slogin
Thursday, September 18, 2008

Wednesday, September 10, 2008
Special Dyes and Lighting Kill MRSA, Research Shows
But new technologies don't replace basic infection control procedures, expert says
By Steven Reinberg, HealthDay Reporter
WEDNESDAY, Sept. 10 (HealthDay News) -- A new kind of paint that releases titanium dioxide when exposed to fluorescent light and a green dye for wounds that gives off toxic molecules when activated by near-infrared light could both kill the deadly superbug known as MRSA, two new studies claim.
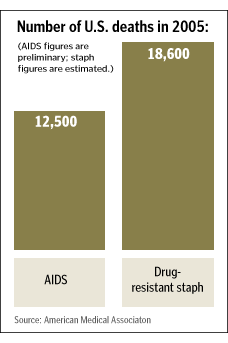
MRSA stands for methicillin-resistant Staphylococcus aureus. It's a strain of staph that's resistant to many antibiotics commonly used to treat it, and it can be fatal. Both reports were presented Tuesday at the Society for General Microbiology Autumn meeting at Trinity College in Dublin.
In the first study, British researcher Lucia Caballero, from Manchester Metropolitan University, found that paint that contained particles of titanium dioxide killed bacteria when it absorbed ultraviolet light.
"If this turns out, the impact is sure to be positive in the area of health," Caballero said.
The same reaction occurs when paints containing titanium dioxide are exposed to infrared light. The researchers found that the paint containing titanium dioxide successfully killed bacteria when the concentration of these nanoparticles was stronger than the normal paint. In fact, they found that all E. coli were killed with fluorescent lights.
"There are many circumstances where it is necessary or desirable to remove or to kill microorganisms found in a biological host or on surfaces," Caballero said. "Maintenance of hygienic standards is essential in hospitals, pharma and the food industry. Surface hygiene could be improved by the action of fluorescent light on catalytic surfaces, such as paints containing nanotitanium, for retarding contamination and saving on cost of cleaning maintenance."
In the second report, Dr. Ghada Omar, from University College London, found that 99 percent of the MRSA bacteria in infected wounds could be killed using a green dye that gives off toxic molecules when activated by infrared light.
"The chemicals produced when the dye is activated harm the bacteria in such a wide variety of ways that it is unlikely bacteria could ever develop resistance to the treatment," Omar said in a statement. "This makes it ideal, and possibly the only option, for treating infections with multiple drug-resistant bacteria, including MRSA."
Infected wounds are a major problem for thousands of hospital patients. Up to 9 percent of hospital-acquired infections occur during surgery and contribute to 77 percent of deaths from operations. These infections increase the length of time patients remain in hospital and increase costs, Omar noted.
Dr. Pascal James Imperato, Dean and Distinguished Service Professor of the Graduate Program in Public Health at SUNY Downstate Medical Center in Brooklyn, said a lot more work needs to be done before these technologies become practical.
"It's very much in the experimental stage at this point," Imperato said. "It's an interesting new development, but one is going to have to see many more studies to determine whether or not this is really going to work."
Dr. Marc Siegel, an associate professor of medicine at New York University School of Medicine, thinks that basic cleanliness can do more to remove the threat of hospital infections than these new technologies.
"This technology is very promising, but it gets us away from the real issue, which is that we have a problem with cleanliness and sterility in hospitals," Siegel said. "The real issue is that doctors don't change their coats, change their gloves enough. We are not using hand wipes."
Siegel noted that soap and water, when used properly, gets rid of most of this bacteria.
"MRSA has been around for 20 years and is a symptom of our inability to properly clean and sterilize facilities, while, at the same time, we are overusing antibiotics," Siegel said.
For more on MRSA, visit the U.S. Centers for Disease Control and Prevention.
SOURCES: Lucia Caballero, Manchester Metropolitan University, U.K.; Marc Siegel, M.D., associate professor, medicine, New York University School of Medicine, New York City, and author, Bird Flu: Everything You Need to Know About the Next Pandemic; Pascal James Imperato, M.D., M.P.H., dean and distinguished service professor, Graduate Program in Public Health, SUNY Downstate Medical Center, Brooklyn, New York; Sept, 9, 2008, presentations, Society for General Microbiology Autumn meeting, Trinity College, Dublin
By Steven Reinberg, HealthDay Reporter
WEDNESDAY, Sept. 10 (HealthDay News) -- A new kind of paint that releases titanium dioxide when exposed to fluorescent light and a green dye for wounds that gives off toxic molecules when activated by near-infrared light could both kill the deadly superbug known as MRSA, two new studies claim.
MRSA stands for methicillin-resistant Staphylococcus aureus. It's a strain of staph that's resistant to many antibiotics commonly used to treat it, and it can be fatal. Both reports were presented Tuesday at the Society for General Microbiology Autumn meeting at Trinity College in Dublin.
In the first study, British researcher Lucia Caballero, from Manchester Metropolitan University, found that paint that contained particles of titanium dioxide killed bacteria when it absorbed ultraviolet light.
"If this turns out, the impact is sure to be positive in the area of health," Caballero said.
The same reaction occurs when paints containing titanium dioxide are exposed to infrared light. The researchers found that the paint containing titanium dioxide successfully killed bacteria when the concentration of these nanoparticles was stronger than the normal paint. In fact, they found that all E. coli were killed with fluorescent lights.
"There are many circumstances where it is necessary or desirable to remove or to kill microorganisms found in a biological host or on surfaces," Caballero said. "Maintenance of hygienic standards is essential in hospitals, pharma and the food industry. Surface hygiene could be improved by the action of fluorescent light on catalytic surfaces, such as paints containing nanotitanium, for retarding contamination and saving on cost of cleaning maintenance."
In the second report, Dr. Ghada Omar, from University College London, found that 99 percent of the MRSA bacteria in infected wounds could be killed using a green dye that gives off toxic molecules when activated by infrared light.
"The chemicals produced when the dye is activated harm the bacteria in such a wide variety of ways that it is unlikely bacteria could ever develop resistance to the treatment," Omar said in a statement. "This makes it ideal, and possibly the only option, for treating infections with multiple drug-resistant bacteria, including MRSA."
Infected wounds are a major problem for thousands of hospital patients. Up to 9 percent of hospital-acquired infections occur during surgery and contribute to 77 percent of deaths from operations. These infections increase the length of time patients remain in hospital and increase costs, Omar noted.
Dr. Pascal James Imperato, Dean and Distinguished Service Professor of the Graduate Program in Public Health at SUNY Downstate Medical Center in Brooklyn, said a lot more work needs to be done before these technologies become practical.
"It's very much in the experimental stage at this point," Imperato said. "It's an interesting new development, but one is going to have to see many more studies to determine whether or not this is really going to work."
Dr. Marc Siegel, an associate professor of medicine at New York University School of Medicine, thinks that basic cleanliness can do more to remove the threat of hospital infections than these new technologies.
"This technology is very promising, but it gets us away from the real issue, which is that we have a problem with cleanliness and sterility in hospitals," Siegel said. "The real issue is that doctors don't change their coats, change their gloves enough. We are not using hand wipes."
Siegel noted that soap and water, when used properly, gets rid of most of this bacteria.
"MRSA has been around for 20 years and is a symptom of our inability to properly clean and sterilize facilities, while, at the same time, we are overusing antibiotics," Siegel said.
For more on MRSA, visit the U.S. Centers for Disease Control and Prevention.
SOURCES: Lucia Caballero, Manchester Metropolitan University, U.K.; Marc Siegel, M.D., associate professor, medicine, New York University School of Medicine, New York City, and author, Bird Flu: Everything You Need to Know About the Next Pandemic; Pascal James Imperato, M.D., M.P.H., dean and distinguished service professor, Graduate Program in Public Health, SUNY Downstate Medical Center, Brooklyn, New York; Sept, 9, 2008, presentations, Society for General Microbiology Autumn meeting, Trinity College, Dublin
Monday, September 8, 2008
A Real Look at the Joint Commission
Value of hospital accreditations under review
By YAMIL BERARD yberard@star-telegram.com
Christine Cahill, a government inspector, walked in to the operating room of a Los Angeles county hospital and found a technician cleaning a surgical instrument. He told her that he had just washed it, but she noticed no water in the sink, so she questioned how he had cleaned it, and he said he had used a cleaner that was in a bottle on the shelf.
"Give me a Q-Tip," she said. She shoved it into the hollow bore of the instrument.
"Out came this crud," she recalled. It was dried-up fragments of bone and blood.
At one out of every three hospitals Cahill surveyed for the federal government in California from 2004-06, she said she found egregious deficiencies that put patients’ lives at risk. Yet these same hospitals, within a year before her review, had received passing grades from the Joint Commission, America’s top healthcare evaluator.
It gave its most prestigious honor — its trademark Gold Seal of Approval — to Martin Luther King Jr./Drew Medical Center, where Cahill found the filthy surgical instrument.
And the commission also awarded that top honor, symbolizing that a hospital has met the most rigorous standards for patient care and safety, to John Peter Smith Hospital in Fort Worth in spring 2006 — the year before an independent consultant documented pervasive problems that put patients at risk.
Now, the Joint Commission itself is under review. For the first time in three decades, Congress is requiring the commission to reapply for authority to certify that hospitals meet federal standards. The commission has a virtual monopoly on hospital accreditation; 88 percent of the nation’s hospitals now choose it over a state agency.
The commission isn’t flinching over the new requirement. It posted a statement on its Web site saying it "is confident that it will receive deeming authority."
But Congress’ rare move opens up the application process to other organizations — including one in Houston that is drawing the interest of a number of Texas hospitals. Some member hospitals are griping that commission reviews often depart from Medicare standards, creating more compliance work.
For critics who characterize the relationship between the commission and client hospitals as too cozy, there couldn’t be a better time to shake up the status quo.
The situation resembles a "country-club-like setting," said Dr. Sidney Wolfe, director of Public Citizen’s Health Research Group in Washington, D.C., a consumers group. "What’s the point of having a regulator that’s a cheerleader over the institution they are supposed to be regulating?"
Scandals also fired up congressional debate last year involving the value of the commission’s accreditation. At issue were cases of accredited hospitals where patients got grossly inadequate treatment. One was a 14-bed West Texas facility where a patient died and federal officials reported that numerous staff members did not have adequate training for the medical procedures they were performing.
As a response to critics, the commission has been working in recent years to beef up its reviews. So-called unannounced visits — in which hospitals are given 48 hours’ warning — began a few years ago. Surveyors now track patients in the operating room and question doctors about diagnoses. What’s more, the agency responds not only to patient concerns, but to news reports of problems, as they did with JPS.
Commission surveyors arrived unannounced at JPS in June following Star-Telegram reports describing the JPS trauma center as a war zone, operating rooms as chaotic, instruments broken, rooms dirty, linens threadbare. Patients were put at risk when doctors couldn’t locate lab results or get crucial reports from specialists.
"We take all complaints seriously," commission spokeswoman Elizabeth Zhani said.
The inspectors cited a list of deficiencies, including intrusions into patient privacy, use of outdated drugs, filth and a system that could not keep track of narcotics, hospital officials said.
Such disturbing findings don’t mean the accreditation process is flawed, Zhani said.
"Accreditation is just not a [survey] visit," she said. "A lot of people tend to focus on that. We don’t know everything else that goes on."
"We cannot be there 365 days of the year," Zhani said.
But critics say the commission will be hard-pressed to identify a hazard so serious that it will shut down a hospital. It didn’t pull the accreditation from Martin Luther King Jr./Drew Medical Center until a year after Cahill conducted her survey — and the news media highlighted patient deaths tied to staff errors.
The Joint Commission process "in itself is, to say the least, superficial," Cahill said. "It doesn’t tell you what the hospital is doing."
Survey problems
The Joint Commission’s plan of attack has always been to "peer-review" or educate hospitals about quality standards, not regulate them, Zhani said.
"Organizations who contract with the Joint Commission are voluntarily saying: 'We want you to come in and survey us and inspect us to see if we’re following your standards for patient care,’ " Zhani said. "They are making a commitment that they want to focus on quality improvement."
But even supporters say the survey process has weaknesses.
Hospitals, no matter the size, are surveyed at least every three years. And the inspectors — usually independent contractors, not commission employees — spend about three days, often in back-to-back interviews with hospital administrators. Some say that doesn’t allow sufficient time for investigation.
At times, medical records are reviewed to make sure the proper documentation is there, not that patients received the proper medication, critics say. The focus of the surveys is on process rather than outcome, said Emily Moreno, a San Antonio registered nurse, now retired, who spent 30 years doing quality assurance at hospitals.
Even at that, though, a surveyor might have found what the JPS consultant did — that up to 20 percent of all medical records were missing.
It also isn’t clear to what degree hospital officials direct surveyors to departments or whether surveyors can — or have time to — wander around and just freely observe. That could explain why troubling problems were apparently overlooked at JPS.
Because the Joint Commission doesn’t make its reports available to the public, patients can’t be assured that surveyors visited some of the less conspicuous areas of the hospital, such as the unit that houses Tarrant County Jail inmates.
An independent consultant in 2007 noted a "dungeon like feel" to the unit and said that infectious patients were housed with noninfectious ones, with the potential of exposing patients, staff and sheriff’s deputies to such diseases as tuberculosis. Staff members told the consultant that the toilets were usually dirty and smelly, garbage cans regularly overflowed. Furniture was broken, and workspaces put doctors and nurses at risk of attack.
The Star-Telegram was not able to interview commission inspectors, despite repeated attempts.
When the survey turns up deficiencies, the commission works with hospitals to help them meet standards. And the commission continues to unveil better methods of identifying patient safety risks. One is a new practice in which surveyors "trace" or follow patients in surgery and other critical services in order to look for vulnerabilities in a hospital’s management of their care.
But critics say that the Joint Commission has other interests that may trump patient safety and lead the commission to stymie efforts that would strengthen compliance and public awareness of hospital problems.
For one, it relies on hospitals for the lion’s share of its $108 million in revenue. Hospitals pay tens of thousands of dollars for their survey evaluations. What’s more, the commission sells its consulting services to help hospitals meet accreditation standards. That boosts sales and creates the potential for conflicts of interest.
"It’s basically run by the [hospital] industry," said Julia Greene, a healthcare professional in Chicago with the Service Employees International Union, which has 2 million members, including the nation’s largest healthcare union.
Among those seeking change is the American Nurses Association, which blames the U.S. Department of Health and Human Services for failing to adequately supervise the commission’s role in the accreditation of hospitals.
Pressure is also coming from some groups concerned about rising healthcare costs. Business groups and insurers want to know if they are getting effective care for their money.
The Office of the Inspector General of DHHS is also expected to add fuel to the fire to revamp the commission. By winter, it is expected to release an examination of the commission’s accreditation process. The inspector general last reviewed the nonprofit in a scathing 1999 report that said its inspections were superficial and left little time for real scrutiny of a hospital’s errant practitioners — the ones most apt to do harm to patients.
Checks and balances
The government does provide some checks and balances to the commission in the form of federal validation surveys, such as Cahill’s at Martin Luther King Jr./Drew, which closed in August 2007 because of substandard conditions.
The surveys are conducted to validate the processes of the commission — "to make sure they’re doing what they’re supposed to be doing," Cahill said.
At most, only 5 percent of the nation’s hospitals undergo the federal scrutiny each year, she said.
But they always involve a team of specialists who spend a longer period studying a hospital, relying on a set of 19 health quality "conditions" required under Medicare regulations. For the MLK Jr./Drew Medical Center survey, Cahill was teamed with pharmacists, nutritionists, nurses and physicians. The surveys can last up to five days, and surveyors can visit the hospital four or five times to check to see that the hospital has corrected problems.
"When [government inspectors] do a validation survey based on the federal regulations, they are very, very thorough and the survey process is a much better process at finding problems than the Joint Commission would ever be," Cahill said.
While inspectors will suggest ways to improve, the survey is intended to root out bad practices, Cahill said.
If a medical record is reviewed, for example, government inspectors observe the patient’s care to see if the practice matches the hospital’s policy and federal standards, she said.
"We probe it further until we are convinced that it’s not an issue or it is an issue," she said.
That’s how inspectors found the case of a meningitis patient who had mistakenly received a potent anticancer drug for four days at the Los Angeles hospital.
Patients may also get some protection from state enforcement agencies. In June, Texas health inspectors were quick to arrive at JPS after news reports drew the commission back for a closer look. State inspectors are closer to the action and can add more layers of protection, the DHHS inspector general reported in 2000.
And next year, there may be a new face or two arriving to accredit hospitals in Texas. A Houston-based accreditation company — DNV Healthcare — is drawing the interest of a number of hospitals who say the commission’s standards deviate too far from Medicare rules.
The commission may have to reckon with the idea that, over time, it could lose its virtual monopoly on accreditation.
That’s all right with the Texas Hospital Association.
Competition "is a good thing . . .," says Starr West, senior director of policy analysis for the association.
"This sort of levels the playing field. We’ve been very supportive of having competition . . . it kind of keeps everybody in line."
Changes in hospitals sought Consumer advocates and other critics are pressing the Joint Commission to strengthen public accountability of hospitals. These are some of the changes being sought.
1 Disclose more information, including life-threatening medical errors and hospital deficiencies.
A commission manual states that hospitals are "encouraged" to report sentinel events, including patient suicide, abduction of newborns, foreign objects left in patients’ bodies during surgery and other major events. But hospitals are not required to do so. When a hospital does report, the commission usually does not identify it to the public. A national snapshot of reported sentinel events on the Joint Commission Web site shows just a map of the number of incidents by state.
Releasing the names of hospitals where sentinel events occurred would be a small step in protecting the public, said Lisa McGiffert, senior policy analyst at Consumers Union in Austin, which publishes Consumer Reports. But even that wouldn’t provide the public with information it needs, she said. For example, the Centers for Disease Control and Prevention estimates that almost 100,000 people die of hospital-acquired infections each year, yet in the past 13 years, the Joint Commission has classified only 105 cases as sentinel events, she said.
"If these sentinel events weren’t so misleading to the public, it’d be laughable," McGiffert said.
"The public has this belief that someone else is watching and making sure that hospitals are safe, and they are mistaken. Nobody is watching."
2 Make survey reports available to the public.
On its Web site, the commission publishes "Quality Reports" that compare a hospital’s performance in a handful of areas to that of other hospitals. For example, John Peter Smith Hospital’s report shows that in 2007 it rated below most accredited hospitals in the country when it comes to heart attack care. ( www.qualitycheck.org/qualityreport.aspx?hcoid=9048#)
But it’s left up to hospitals to decide whether to disclose deficiencies noted by surveyors. After commission inspectors paid a surprise visit to JPS this summer, the hospital made public some findings but did not release the report and specific deficiencies.
"If the organization wants to release the report, they can release it," Joint Commission spokeswoman Elizabeth Zhani said.
3 Pay more heed to patient complaints.
Emily Moreno of San Antonio, who focused on hospital quality during her 30 years as a registered nurse, filed a complaint with the commission after she developed an infection at the site of a breast biopsy at an Oklahoma City hospital. The commission had accredited the hospital seven months earlier.
It took no action on her complaint, she said. It only told her, in response, that it gives "serious consideration" to all complaints.
Susan Sheridan, an Idaho mother of a child with cerebral palsy, did get the commission’s attention. Her son, now 13, suffered brain damage because of the failure of hospitals to test newborns for jaundice. She and other mothers of children with cerebral palsy co-founded Parents of Infants of Children with Kernicterus. Thanks to her advocacy, hospitals now test for excessive bilirubin levels in newborns.
4 Place more patient representatives on the commission board.
Sheridan would also like to see the commission open up more hospital data to the public, but doesn’t believe that will happen soon.
"Their very structure stifles that," she said. Most of its board members are doctors or health practitioners.
"What ties their hands basically is that its members and their clients are hospitals," she said.
By YAMIL BERARD yberard@star-telegram.com
Christine Cahill, a government inspector, walked in to the operating room of a Los Angeles county hospital and found a technician cleaning a surgical instrument. He told her that he had just washed it, but she noticed no water in the sink, so she questioned how he had cleaned it, and he said he had used a cleaner that was in a bottle on the shelf.
"Give me a Q-Tip," she said. She shoved it into the hollow bore of the instrument.
"Out came this crud," she recalled. It was dried-up fragments of bone and blood.
At one out of every three hospitals Cahill surveyed for the federal government in California from 2004-06, she said she found egregious deficiencies that put patients’ lives at risk. Yet these same hospitals, within a year before her review, had received passing grades from the Joint Commission, America’s top healthcare evaluator.
It gave its most prestigious honor — its trademark Gold Seal of Approval — to Martin Luther King Jr./Drew Medical Center, where Cahill found the filthy surgical instrument.
And the commission also awarded that top honor, symbolizing that a hospital has met the most rigorous standards for patient care and safety, to John Peter Smith Hospital in Fort Worth in spring 2006 — the year before an independent consultant documented pervasive problems that put patients at risk.
Now, the Joint Commission itself is under review. For the first time in three decades, Congress is requiring the commission to reapply for authority to certify that hospitals meet federal standards. The commission has a virtual monopoly on hospital accreditation; 88 percent of the nation’s hospitals now choose it over a state agency.
The commission isn’t flinching over the new requirement. It posted a statement on its Web site saying it "is confident that it will receive deeming authority."
But Congress’ rare move opens up the application process to other organizations — including one in Houston that is drawing the interest of a number of Texas hospitals. Some member hospitals are griping that commission reviews often depart from Medicare standards, creating more compliance work.
For critics who characterize the relationship between the commission and client hospitals as too cozy, there couldn’t be a better time to shake up the status quo.
The situation resembles a "country-club-like setting," said Dr. Sidney Wolfe, director of Public Citizen’s Health Research Group in Washington, D.C., a consumers group. "What’s the point of having a regulator that’s a cheerleader over the institution they are supposed to be regulating?"
Scandals also fired up congressional debate last year involving the value of the commission’s accreditation. At issue were cases of accredited hospitals where patients got grossly inadequate treatment. One was a 14-bed West Texas facility where a patient died and federal officials reported that numerous staff members did not have adequate training for the medical procedures they were performing.
As a response to critics, the commission has been working in recent years to beef up its reviews. So-called unannounced visits — in which hospitals are given 48 hours’ warning — began a few years ago. Surveyors now track patients in the operating room and question doctors about diagnoses. What’s more, the agency responds not only to patient concerns, but to news reports of problems, as they did with JPS.
Commission surveyors arrived unannounced at JPS in June following Star-Telegram reports describing the JPS trauma center as a war zone, operating rooms as chaotic, instruments broken, rooms dirty, linens threadbare. Patients were put at risk when doctors couldn’t locate lab results or get crucial reports from specialists.
"We take all complaints seriously," commission spokeswoman Elizabeth Zhani said.
The inspectors cited a list of deficiencies, including intrusions into patient privacy, use of outdated drugs, filth and a system that could not keep track of narcotics, hospital officials said.
Such disturbing findings don’t mean the accreditation process is flawed, Zhani said.
"Accreditation is just not a [survey] visit," she said. "A lot of people tend to focus on that. We don’t know everything else that goes on."
"We cannot be there 365 days of the year," Zhani said.
But critics say the commission will be hard-pressed to identify a hazard so serious that it will shut down a hospital. It didn’t pull the accreditation from Martin Luther King Jr./Drew Medical Center until a year after Cahill conducted her survey — and the news media highlighted patient deaths tied to staff errors.
The Joint Commission process "in itself is, to say the least, superficial," Cahill said. "It doesn’t tell you what the hospital is doing."
Survey problems
The Joint Commission’s plan of attack has always been to "peer-review" or educate hospitals about quality standards, not regulate them, Zhani said.
"Organizations who contract with the Joint Commission are voluntarily saying: 'We want you to come in and survey us and inspect us to see if we’re following your standards for patient care,’ " Zhani said. "They are making a commitment that they want to focus on quality improvement."
But even supporters say the survey process has weaknesses.
Hospitals, no matter the size, are surveyed at least every three years. And the inspectors — usually independent contractors, not commission employees — spend about three days, often in back-to-back interviews with hospital administrators. Some say that doesn’t allow sufficient time for investigation.
At times, medical records are reviewed to make sure the proper documentation is there, not that patients received the proper medication, critics say. The focus of the surveys is on process rather than outcome, said Emily Moreno, a San Antonio registered nurse, now retired, who spent 30 years doing quality assurance at hospitals.
Even at that, though, a surveyor might have found what the JPS consultant did — that up to 20 percent of all medical records were missing.
It also isn’t clear to what degree hospital officials direct surveyors to departments or whether surveyors can — or have time to — wander around and just freely observe. That could explain why troubling problems were apparently overlooked at JPS.
Because the Joint Commission doesn’t make its reports available to the public, patients can’t be assured that surveyors visited some of the less conspicuous areas of the hospital, such as the unit that houses Tarrant County Jail inmates.
An independent consultant in 2007 noted a "dungeon like feel" to the unit and said that infectious patients were housed with noninfectious ones, with the potential of exposing patients, staff and sheriff’s deputies to such diseases as tuberculosis. Staff members told the consultant that the toilets were usually dirty and smelly, garbage cans regularly overflowed. Furniture was broken, and workspaces put doctors and nurses at risk of attack.
The Star-Telegram was not able to interview commission inspectors, despite repeated attempts.
When the survey turns up deficiencies, the commission works with hospitals to help them meet standards. And the commission continues to unveil better methods of identifying patient safety risks. One is a new practice in which surveyors "trace" or follow patients in surgery and other critical services in order to look for vulnerabilities in a hospital’s management of their care.
But critics say that the Joint Commission has other interests that may trump patient safety and lead the commission to stymie efforts that would strengthen compliance and public awareness of hospital problems.
For one, it relies on hospitals for the lion’s share of its $108 million in revenue. Hospitals pay tens of thousands of dollars for their survey evaluations. What’s more, the commission sells its consulting services to help hospitals meet accreditation standards. That boosts sales and creates the potential for conflicts of interest.
"It’s basically run by the [hospital] industry," said Julia Greene, a healthcare professional in Chicago with the Service Employees International Union, which has 2 million members, including the nation’s largest healthcare union.
Among those seeking change is the American Nurses Association, which blames the U.S. Department of Health and Human Services for failing to adequately supervise the commission’s role in the accreditation of hospitals.
Pressure is also coming from some groups concerned about rising healthcare costs. Business groups and insurers want to know if they are getting effective care for their money.
The Office of the Inspector General of DHHS is also expected to add fuel to the fire to revamp the commission. By winter, it is expected to release an examination of the commission’s accreditation process. The inspector general last reviewed the nonprofit in a scathing 1999 report that said its inspections were superficial and left little time for real scrutiny of a hospital’s errant practitioners — the ones most apt to do harm to patients.
Checks and balances
The government does provide some checks and balances to the commission in the form of federal validation surveys, such as Cahill’s at Martin Luther King Jr./Drew, which closed in August 2007 because of substandard conditions.
The surveys are conducted to validate the processes of the commission — "to make sure they’re doing what they’re supposed to be doing," Cahill said.
At most, only 5 percent of the nation’s hospitals undergo the federal scrutiny each year, she said.
But they always involve a team of specialists who spend a longer period studying a hospital, relying on a set of 19 health quality "conditions" required under Medicare regulations. For the MLK Jr./Drew Medical Center survey, Cahill was teamed with pharmacists, nutritionists, nurses and physicians. The surveys can last up to five days, and surveyors can visit the hospital four or five times to check to see that the hospital has corrected problems.
"When [government inspectors] do a validation survey based on the federal regulations, they are very, very thorough and the survey process is a much better process at finding problems than the Joint Commission would ever be," Cahill said.
While inspectors will suggest ways to improve, the survey is intended to root out bad practices, Cahill said.
If a medical record is reviewed, for example, government inspectors observe the patient’s care to see if the practice matches the hospital’s policy and federal standards, she said.
"We probe it further until we are convinced that it’s not an issue or it is an issue," she said.
That’s how inspectors found the case of a meningitis patient who had mistakenly received a potent anticancer drug for four days at the Los Angeles hospital.
Patients may also get some protection from state enforcement agencies. In June, Texas health inspectors were quick to arrive at JPS after news reports drew the commission back for a closer look. State inspectors are closer to the action and can add more layers of protection, the DHHS inspector general reported in 2000.
And next year, there may be a new face or two arriving to accredit hospitals in Texas. A Houston-based accreditation company — DNV Healthcare — is drawing the interest of a number of hospitals who say the commission’s standards deviate too far from Medicare rules.
The commission may have to reckon with the idea that, over time, it could lose its virtual monopoly on accreditation.
That’s all right with the Texas Hospital Association.
Competition "is a good thing . . .," says Starr West, senior director of policy analysis for the association.
"This sort of levels the playing field. We’ve been very supportive of having competition . . . it kind of keeps everybody in line."
Changes in hospitals sought Consumer advocates and other critics are pressing the Joint Commission to strengthen public accountability of hospitals. These are some of the changes being sought.
1 Disclose more information, including life-threatening medical errors and hospital deficiencies.
A commission manual states that hospitals are "encouraged" to report sentinel events, including patient suicide, abduction of newborns, foreign objects left in patients’ bodies during surgery and other major events. But hospitals are not required to do so. When a hospital does report, the commission usually does not identify it to the public. A national snapshot of reported sentinel events on the Joint Commission Web site shows just a map of the number of incidents by state.
Releasing the names of hospitals where sentinel events occurred would be a small step in protecting the public, said Lisa McGiffert, senior policy analyst at Consumers Union in Austin, which publishes Consumer Reports. But even that wouldn’t provide the public with information it needs, she said. For example, the Centers for Disease Control and Prevention estimates that almost 100,000 people die of hospital-acquired infections each year, yet in the past 13 years, the Joint Commission has classified only 105 cases as sentinel events, she said.
"If these sentinel events weren’t so misleading to the public, it’d be laughable," McGiffert said.
"The public has this belief that someone else is watching and making sure that hospitals are safe, and they are mistaken. Nobody is watching."
2 Make survey reports available to the public.
On its Web site, the commission publishes "Quality Reports" that compare a hospital’s performance in a handful of areas to that of other hospitals. For example, John Peter Smith Hospital’s report shows that in 2007 it rated below most accredited hospitals in the country when it comes to heart attack care. ( www.qualitycheck.org/qualityreport.aspx?hcoid=9048#)
But it’s left up to hospitals to decide whether to disclose deficiencies noted by surveyors. After commission inspectors paid a surprise visit to JPS this summer, the hospital made public some findings but did not release the report and specific deficiencies.
"If the organization wants to release the report, they can release it," Joint Commission spokeswoman Elizabeth Zhani said.
3 Pay more heed to patient complaints.
Emily Moreno of San Antonio, who focused on hospital quality during her 30 years as a registered nurse, filed a complaint with the commission after she developed an infection at the site of a breast biopsy at an Oklahoma City hospital. The commission had accredited the hospital seven months earlier.
It took no action on her complaint, she said. It only told her, in response, that it gives "serious consideration" to all complaints.
Susan Sheridan, an Idaho mother of a child with cerebral palsy, did get the commission’s attention. Her son, now 13, suffered brain damage because of the failure of hospitals to test newborns for jaundice. She and other mothers of children with cerebral palsy co-founded Parents of Infants of Children with Kernicterus. Thanks to her advocacy, hospitals now test for excessive bilirubin levels in newborns.
4 Place more patient representatives on the commission board.
Sheridan would also like to see the commission open up more hospital data to the public, but doesn’t believe that will happen soon.
"Their very structure stifles that," she said. Most of its board members are doctors or health practitioners.
"What ties their hands basically is that its members and their clients are hospitals," she said.
Tuesday, August 19, 2008
Public Pressure Is Working
 7 SoCal Hospitals Fined For Medical Errors
KTLA News August 18, 2008, 8:58 PM PDT
LOS ANGELES -- Seven hospitals in L.A. and Orange counties were fined today by the state for mistakes that included leaving surgical tools in patients and over-medicating a patient.
"Ensuring all Californians receive quality patient care is our top priority," said Kathleen Billingsley, deputy director of the Center for Health Care Quality with the California Department of Public Health.
Statewide, fines were levied against a total of 18 hospitals -- some of which had multiple violations -- for "incidents that caused, or were likely to cause, serious injury or death to patients."
Harbor-UCLA Medical Center in Torrance was fined $25,000 for failing to accurately label tissue specimens, which led to unnecessary surgery for one patient and delayed treatment for another, according to DPH. The hospital received a second $25,000 penalty for failing to provide screening examinations and stabilizing medical care in a timely manner for two patients, according to the state healthcare agency.
Los Angeles County-USC Medical Center was fined $25,000 for not providing adequate nursing staff for a suicide watch to meet the needs of a patient, DPH found.
Five hospitals in Orange County were fined $25,000 per violation cited by the state.
Anaheim General Hospital received two violations for failing to ensure medical devices were electronically safe and for failing to maintain the pharmacy's refrigerated temperatures.
Coastal Communities Hospital in Santa Ana was fined for over-medicating a patient, resulting in death.
At Fountain Valley Regional Hospital, doctors left a sponge in a patient following surgery.
At Hoag Memorial Hospital Presbyterian in Newport Beach, hospital staff left a surgical instrument in a patient.
At Los Alamitos Medical Center, a patient died after falling out of a wheelchair. State regulators found hospital staff failed to buckle the person into the chair.
The hospitals may appeal the penalties by requesting a hearing within 10 days of notification.
Friday, August 15, 2008
How to stop Hospital Infections
Fox11 News in Los Angeles reports on the very disturbing trend of more and more patients picking up stubborn, dangerous infections while in the hospital. Such was the case with necrotizing fasciitis Survivor Alicia Cole. Now Dr. Alfonso Torres Cook is fighting back against infections using a common-sense plan of attack, and drugs have nothing to do with it. More hospitals should follow his lead.
Wednesday, July 9, 2008
Anonymous Protection?
No hospitals named in tales of infection
Report on diseases acquired during medical procedures keeps institutions anonymous
By CATHLEEN F. CROWLEY, Staff writer First published: Wednesday, July 9, 2008
ALBANY -- Three years after a law requiring hospitals to report their infection rates to the state passed, the numbers have been released -- sort of.
The hospital-by-hospital rates for 2007 will not be fully disclosed. Instead, New Yorkers can see aggregate rates, an interim step negotiated by the hospital industry when the law was enacted in 2005.
"The promise that was made to (the hospital community) was we will do this right," said Assemblyman Richard Gottfried, chairman of the Assembly Health Committee, "to make sure it's running right before we take it public. That was an important promise and a smart promise."
The hospital-specific numbers will be revealed next year and every year thereafter. Meanwhile, the public can view the 2007 hospital-by-hospital rates on the state Department of Health's Web site, http://www.nyhealth.gov, but the names of the hospitals are masked.
According to the federal Centers for Disease Control and Prevention, there were an estimated 1.7 million health care-associated infections nationally and 99,000 deaths from those infections in 2002. Hospital-acquired infections are considered preventable with good hand-washing, equipment sterilization and proper procedures.
Capital Region hospitals refused a request from the Times Union to voluntarily release their infection rates on Tuesday, saying they will follow the state's timeline for unveiling the information.
"It allows us and all hospitals to take a look at the statewide data and compare it to make sure it's accurate and complete and we are all comparing apples to apples," said Brad Sexauer, Saratoga Hospital's vice president of strategy and marketing development.
Arthur Levin, director of the Center for Medical Consumers and a member of the state's advisory board for the reporting system, defended the anonymity granted to hospitals this year.
Levin said it will assure that the data is accurate, and next year, "hospitals will have no excuses."
According to the aggregate figures released Tuesday, New York's infection rates mirror the nation's. For every 100 people who undergo colon surgery, about six get an infection, according to the report. For people who have a coronary bypass graft, 3.6 out of every 100 get an infection. Fewer than 1 percent develop infections related to central lines, which are tubes that snake through a vein to the heart to deliver medicine and monitor heart function.
Of all reported infections, about 10 percent were caused by methicillin-resistant Staphylococcus aureus or MRSA. The rest were caused by organisms that respond more easily to antibiotics.
Betsy McCaughey, the former New York lieutenant governor who has since founded the Committee to Reduce Infection Deaths, said the report has many shortcomings -- most notably the comparison to national rates.
"The only infection rate that is acceptable is zero," McCaughey said.
McCaughey criticized the report for highlighting risk factors for infections, like gender and obesity, without exploring the most important contributors: unclean hospitals and lax procedures.
Report on diseases acquired during medical procedures keeps institutions anonymous
By CATHLEEN F. CROWLEY, Staff writer First published: Wednesday, July 9, 2008
ALBANY -- Three years after a law requiring hospitals to report their infection rates to the state passed, the numbers have been released -- sort of.
The hospital-by-hospital rates for 2007 will not be fully disclosed. Instead, New Yorkers can see aggregate rates, an interim step negotiated by the hospital industry when the law was enacted in 2005.
"The promise that was made to (the hospital community) was we will do this right," said Assemblyman Richard Gottfried, chairman of the Assembly Health Committee, "to make sure it's running right before we take it public. That was an important promise and a smart promise."
The hospital-specific numbers will be revealed next year and every year thereafter. Meanwhile, the public can view the 2007 hospital-by-hospital rates on the state Department of Health's Web site, http://www.nyhealth.gov, but the names of the hospitals are masked.
According to the federal Centers for Disease Control and Prevention, there were an estimated 1.7 million health care-associated infections nationally and 99,000 deaths from those infections in 2002. Hospital-acquired infections are considered preventable with good hand-washing, equipment sterilization and proper procedures.
Capital Region hospitals refused a request from the Times Union to voluntarily release their infection rates on Tuesday, saying they will follow the state's timeline for unveiling the information.
"It allows us and all hospitals to take a look at the statewide data and compare it to make sure it's accurate and complete and we are all comparing apples to apples," said Brad Sexauer, Saratoga Hospital's vice president of strategy and marketing development.
Arthur Levin, director of the Center for Medical Consumers and a member of the state's advisory board for the reporting system, defended the anonymity granted to hospitals this year.
Levin said it will assure that the data is accurate, and next year, "hospitals will have no excuses."
According to the aggregate figures released Tuesday, New York's infection rates mirror the nation's. For every 100 people who undergo colon surgery, about six get an infection, according to the report. For people who have a coronary bypass graft, 3.6 out of every 100 get an infection. Fewer than 1 percent develop infections related to central lines, which are tubes that snake through a vein to the heart to deliver medicine and monitor heart function.
Of all reported infections, about 10 percent were caused by methicillin-resistant Staphylococcus aureus or MRSA. The rest were caused by organisms that respond more easily to antibiotics.
Betsy McCaughey, the former New York lieutenant governor who has since founded the Committee to Reduce Infection Deaths, said the report has many shortcomings -- most notably the comparison to national rates.
"The only infection rate that is acceptable is zero," McCaughey said.
McCaughey criticized the report for highlighting risk factors for infections, like gender and obesity, without exploring the most important contributors: unclean hospitals and lax procedures.
Monday, July 7, 2008
100 Mistakes A Month
Serious patient errors at California hospitals disclosed in state filings
About 100 Californians a month are being harmed in adverse events considered preventable. A lawmaker proposes banning reimbursements to hospitals for some types of injuries.
By Jordan Rau, Los Angeles Times Staff Writer June 30, 2008
SACRAMENTO -- Last October, a technician at the children's hospital at Stanford University improperly connected a ventilator hose, accidentally pumping too little oxygen into a 9-day-old infant's lungs.
A month later, technicians at Dominican Hospital in Santa Cruz unintentionally placed a CT scan of one patient into the electronic file of another, leading physicians to remove the wrong person’s appendix.
Last March, Virginia Fahres, 76, died at Pomona Valley Hospital Medical Center in Pomona after a nurse gave her two drugs, neither of which her doctor had prescribed.
Those incidents were among 1,002 cases of serious medical harm disclosed by California hospitals between July 2007 and May of this year. The disclosures are the first under a state law that requires hospitals to inform health regulators of all substantial injuries to their patients.
Officially called “adverse events,” those accidents are also known as "never events" because they are considered preventable, and many safety experts say they should never happen. California patients are being injured at a rate of about 100 a month, according to data compiled by the state Department of Public Health.
"I think the never events are a wake-up call to everyone about the safety of California hospitals," said Beth Capell, a lobbyist for Health Access California, a consumer group.
Revelations of such errors have led lawmakers and hospital associations in at least seven states to protect patients from having to pay for the cost of care that went awry. In Sacramento, an assemblyman proposed a ban on reimbursing hospitals for the types of injuries tracked by the state. But when lobbyists for doctors and hospitals objected, he scaled it back to cover far fewer errors.
Four million people were admitted to California hospitals last year. State investigators found some errors occurred because hospitals failed to follow safeguards designed specifically to prevent harm.
Last July at UC San Diego Medical Center, a patient died after a nurse incorrectly programmed a medicine pump that then delivered more than twice the appropriate dose of a specialized blood pressure drug. Regulators found that the hospital's administration had been warned earlier by its own safety committee that "errors continue to occur" with that type of pump but had not taken sufficient corrective action, according to a state probe.
UC San Diego officials said they have since held repeat drills with staffers who treat patients with Flolan and examined every step in the process.
Dr. Angela Scioscia, the center's senior medical director, said the public reporting requirement is "a great opportunity to make rapid improvements" because hospitals can learn from one another's problems. "We don't want people to be afraid when they come into hospitals, because they are becoming safer and safer all the time," Scioscia said.
Under the 2006 disclosure law by state Sen. Elaine Alquist (D-Santa Clara), hospitals must inform state regulators of every occurrence of 28 different types of dangerous mistakes. Those include deaths during labor, medication errors, suicide attempts and sexual assaults.
The public health department has until 2015 to begin posting the information on the Internet, although officials said they hope to begin publishing it earlier. The most recent figures available cover the 10 months since July 2007. In that time, 466 patients developed bedsores so severe that the dead skin formed a crater or rotted through to the muscle or bone.
Another 145 patients had foreign objects such as surgical equipment left in their bodies. Thirty-four died while under anesthesia. In 41 surgeries, doctors performed the wrong procedure or operated on the wrong body part or on the wrong patient.
So far, the state Department of Public Health has levied $25,000 fines against 10 hospitals that reported adverse events. Officials said other investigations are still under way.
One hospital, Scripps Memorial in La Jolla, was fined twice for two errors that occurred last November with the same patient. First, as the patient was recovering from surgery, she was given a painkiller that is not supposed to be used after operations. When she went into respiratory arrest, the pharmacist provided a corrective medication at a dose 10 times too weak to be effective.
The patient survived. State investigators discovered that the hospital's pharmacists had not been properly instructed in the use of 10 medications, including the corrective drug, that the hospital stocked for emergencies.
The ventilator error at Stanford's Lucile Packard Children's Hospital occurred because a therapist had assembled the machine by following a diagram that had been drawn backward. Dr. Christy Sandborg, the hospital's chief of staff, said the medical team quickly noticed that the ventilator wasn't working correctly and stopped using it. The child recovered, she said, and the hospital has made changes to prevent future occurrences.
Overcrowded emergency rooms are another factor behind patient injuries. A 2006 study found that California had fewer emergency rooms per resident than any other state.
At Kaiser Foundation Hospital San Jose in March, staffers left a patient waiting in the emergency room for more than an hour after a test showed that his blood sugar was higher than the maximum measurable with a glucometer. The medics determined that he needed immediate care, but all 25 treatment bays were full. He passed out in the waiting room and died from heart failure.
About 100 Californians a month are being harmed in adverse events considered preventable. A lawmaker proposes banning reimbursements to hospitals for some types of injuries.
By Jordan Rau, Los Angeles Times Staff Writer June 30, 2008
SACRAMENTO -- Last October, a technician at the children's hospital at Stanford University improperly connected a ventilator hose, accidentally pumping too little oxygen into a 9-day-old infant's lungs.
A month later, technicians at Dominican Hospital in Santa Cruz unintentionally placed a CT scan of one patient into the electronic file of another, leading physicians to remove the wrong person’s appendix.
Last March, Virginia Fahres, 76, died at Pomona Valley Hospital Medical Center in Pomona after a nurse gave her two drugs, neither of which her doctor had prescribed.
Those incidents were among 1,002 cases of serious medical harm disclosed by California hospitals between July 2007 and May of this year. The disclosures are the first under a state law that requires hospitals to inform health regulators of all substantial injuries to their patients.
Officially called “adverse events,” those accidents are also known as "never events" because they are considered preventable, and many safety experts say they should never happen. California patients are being injured at a rate of about 100 a month, according to data compiled by the state Department of Public Health.
"I think the never events are a wake-up call to everyone about the safety of California hospitals," said Beth Capell, a lobbyist for Health Access California, a consumer group.
Revelations of such errors have led lawmakers and hospital associations in at least seven states to protect patients from having to pay for the cost of care that went awry. In Sacramento, an assemblyman proposed a ban on reimbursing hospitals for the types of injuries tracked by the state. But when lobbyists for doctors and hospitals objected, he scaled it back to cover far fewer errors.
Four million people were admitted to California hospitals last year. State investigators found some errors occurred because hospitals failed to follow safeguards designed specifically to prevent harm.
Last July at UC San Diego Medical Center, a patient died after a nurse incorrectly programmed a medicine pump that then delivered more than twice the appropriate dose of a specialized blood pressure drug. Regulators found that the hospital's administration had been warned earlier by its own safety committee that "errors continue to occur" with that type of pump but had not taken sufficient corrective action, according to a state probe.
UC San Diego officials said they have since held repeat drills with staffers who treat patients with Flolan and examined every step in the process.
Dr. Angela Scioscia, the center's senior medical director, said the public reporting requirement is "a great opportunity to make rapid improvements" because hospitals can learn from one another's problems. "We don't want people to be afraid when they come into hospitals, because they are becoming safer and safer all the time," Scioscia said.
Under the 2006 disclosure law by state Sen. Elaine Alquist (D-Santa Clara), hospitals must inform state regulators of every occurrence of 28 different types of dangerous mistakes. Those include deaths during labor, medication errors, suicide attempts and sexual assaults.
The public health department has until 2015 to begin posting the information on the Internet, although officials said they hope to begin publishing it earlier. The most recent figures available cover the 10 months since July 2007. In that time, 466 patients developed bedsores so severe that the dead skin formed a crater or rotted through to the muscle or bone.
Another 145 patients had foreign objects such as surgical equipment left in their bodies. Thirty-four died while under anesthesia. In 41 surgeries, doctors performed the wrong procedure or operated on the wrong body part or on the wrong patient.
So far, the state Department of Public Health has levied $25,000 fines against 10 hospitals that reported adverse events. Officials said other investigations are still under way.
One hospital, Scripps Memorial in La Jolla, was fined twice for two errors that occurred last November with the same patient. First, as the patient was recovering from surgery, she was given a painkiller that is not supposed to be used after operations. When she went into respiratory arrest, the pharmacist provided a corrective medication at a dose 10 times too weak to be effective.
The patient survived. State investigators discovered that the hospital's pharmacists had not been properly instructed in the use of 10 medications, including the corrective drug, that the hospital stocked for emergencies.
The ventilator error at Stanford's Lucile Packard Children's Hospital occurred because a therapist had assembled the machine by following a diagram that had been drawn backward. Dr. Christy Sandborg, the hospital's chief of staff, said the medical team quickly noticed that the ventilator wasn't working correctly and stopped using it. The child recovered, she said, and the hospital has made changes to prevent future occurrences.
Overcrowded emergency rooms are another factor behind patient injuries. A 2006 study found that California had fewer emergency rooms per resident than any other state.
At Kaiser Foundation Hospital San Jose in March, staffers left a patient waiting in the emergency room for more than an hour after a test showed that his blood sugar was higher than the maximum measurable with a glucometer. The medics determined that he needed immediate care, but all 25 treatment bays were full. He passed out in the waiting room and died from heart failure.
Subscribe to:
Posts (Atom)